
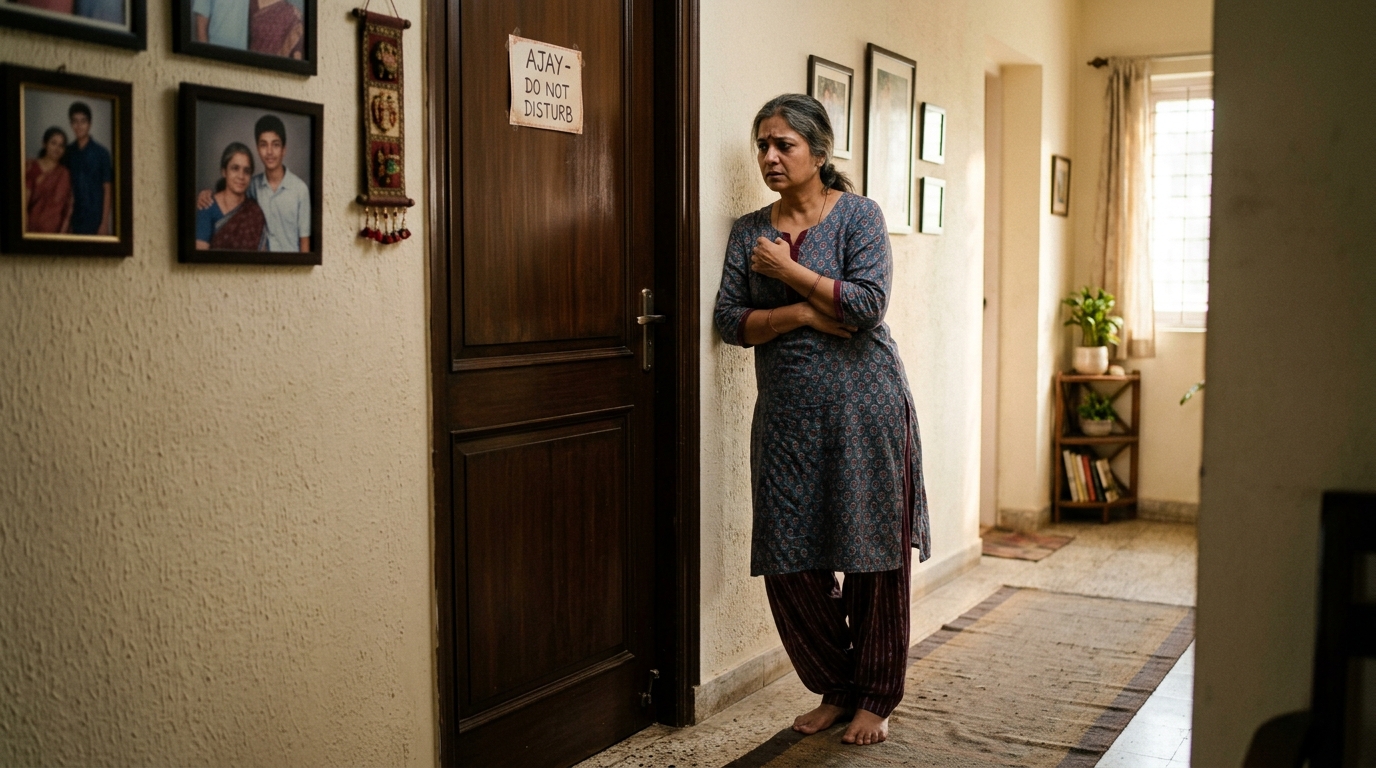
Reviewed by IMPS Editorial Team · Last reviewed
A parent stands outside a closed bedroom door, hand raised, unsure whether to knock and whether these are signs of depression in teenagers. Inside is a Class 10 student who used to drop his bag and head for the kitchen. Now he goes straight to his room after school and snaps at every question, even “did you eat?” The parent wonders whether board exam stress explains it or whether something more is going on.
Most parents in India know this scene, and the hard part is not the moodiness but the uncertainty. The teen years bring real ups and downs, and feelings can swing hard without anything being wrong. Depression is a mental health condition, not a weakness or a discipline problem, and it deserves the same care a family gives to a fever. A parent who reads on will be able to spot the difference, start a conversation with the child and know where to go for help.
That starts with one shift in thinking: understanding why depression is more than a bad mood.
Key Takeaways
- Normal mood swings lift within hours or a day or two; depression lasts two weeks or longer, most days.
- A depressed teen more often looks angry, irritable or physically unwell than sad.
- Three questions settle most cases: how long, how bad and how unlike themselves the teen is.
- Any talk of dying, even as a joke, is an emergency: call 112 or the Tele-MANAS helpline at 14416.
- Punishing phone use or falling marks pushes a depressed teen further away.
- Talk therapy comes first; an antidepressant is added only when needed and watched closely.
- Most teens who get treatment improve within weeks, and the pediatrician or family doctor is the first stop.
Why Teen Depression Is More Than a Bad Mood
A 2024 US survey found over 15 percent of teens aged 12 to 17 had a major depressive episode in the past year. That is roughly one teen in seven, a number far too large to be just moodiness. Teen depression is a serious mood disorder, also called major depression or clinical depression, and it cannot be willed away. It changes how a teen thinks, feels and behaves, and it can cause emotional, functional and physical problems.
A major depressive episode means two weeks or more of low or irritable mood, or lost interest, most of the day almost daily. Several other symptoms come with it and disrupt daily functioning. A doctor may name one of three types: major depression, persistent depressive disorder (also called dysthymia) or bipolar disorder. Most depressed teens never receive help, so silence is the usual outcome, not the exception.
Most teens with depression never get help. Silence is the usual outcome, and a parent who notices is already changing those odds.
A teen who hides in a room for weeks is not being difficult; the disorder is doing the hiding. The reassuring part is that for most teens, symptoms ease with treatment such as talk therapy and medication. Good mental health care gives back the life a teen was losing, one school week at a time. Before judging what is wrong, though, a parent needs a clear picture of what normal mood swings look like.
What Normal Teenage Mood Swings Look Like
A teen slams a door at 6 p.m. over a question about homework and is laughing at the dinner table by 8. That swing is the textbook shape of normal mood swings, exhausting without being alarming. Peer pressure, academic expectations and a changing body bring ups and downs for most teens. Hormones and stress explain an occasional bout of teenage angst, but not continuous, unrelenting unhappiness.
The hallmark of a normal mood swing is that it lifts within hours or a day or two. The teen still enjoys friends, food, games or music once the storm passes. The child who would not speak at 6 can be reached at 8. That reachability is the baseline a parent compares everything else against.
Why hormones and a changing brain cause the ups and downs
Puberty usually begins around ages 10 to 14, and hormone shifts arrive before anyone has practice managing them. The brain matures unevenly: its emotional center develops early, while the part that handles planning and emotional control keeps developing into the mid-20s. Strong feelings outrun self-control in early adolescence for exactly that reason. The gas pedal works years before the brakes do.
Everyday Indian triggers pile on top of the biology. A Class 9 student may have school until 2 p.m., tuition until 7 and homework until midnight, with little time left to simply be a person. Friend-group drama on a class WhatsApp group can turn a good day sour in one message. None of that means something is wrong; it means the day was hard.
What age mood swings usually peak and settle
Many parents find roughly ages 13 to 15 the hardest stretch. The push for independence is strongest then and emotional control is least developed, so clashes over curfews and phones peak. Most teens become noticeably easier to live with again in the late teens, often around 17 to 19, as the brain matures and identity settles. Teenagers do start being nice again, usually before they leave for college.
One exception deserves a closer look: a teen who gets worse rather than better after 16. Moodiness that deepens when it should be easing is not following the normal curve. The signs that come next are the ones that do not lift by dinner.
Signs of Depression in Teenagers That Parents Often Miss
The core signs of depression in teenagers are a persistent change in mood, behavior or body that lasts for weeks and gets in the way of normal life. A sign counts when it is a change from the teen’s previous self and causes trouble at school, at home or with friends. The most common mistake a parent makes is reading heavy phone use or a drop in marks as laziness and responding with punishment. Taking the phone away or adding tuition hours pushes a depressed teen further away.
Some symptoms are easy to miss because they look like ordinary teenage behavior:
- Irritability and snapping rather than visible sadness
- Headaches, stomachaches or body aches with no medical cause
- A formerly good student suddenly frustrated by homework
- Quitting a cricket team, dance class or a long-held hobby
- More hours in bed, including weekend afternoons
- Drifting from old friends to a new, different crowd
Emotional changes
At home, emotional signs show up as crying spells with no apparent reason, anger over small matters, or a flat “nothing matters” about plans. The teen may describe feeling hopeless or empty, talk down about themselves, or circle back to a failure from months ago. Extreme sensitivity to rejection is common, along with a need for constant reassurance after a minor slight. Trouble concentrating and making decisions shows up as unfinished assignments and endless dithering over simple choices.
Frequent thoughts of death may also surface in offhand remarks or in what the teen writes and watches. Loss of interest is one of the clearest emotional signs. Activities that once mattered, from football to gaming to music practice, stop being worth the effort. A parent who hears “I don’t feel like it” every day for weeks is hearing a symptom.
Behavioral changes
Behavior changes are what teachers and friends notice first. Sleep goes wrong in one direction or the other: lying awake until 2 a.m. or sleeping 12 hours and still tired. Appetite shifts, and the teen loses or gains noticeable weight within a term. School performance slides, attendance drops and the teen stops bothering with hygiene or clean clothes.
Some teens become agitated, pacing or wringing their hands; others move and speak more slowly than before. Alcohol or drug use may start as a way to numb the mood. Angry outbursts, risky behavior, reckless driving, unsafe sex and running away or threatening to are all on the list. Self-harm such as cutting or burning, often hidden under long sleeves, needs action the same day.
Physical symptoms
Depression can also live in the body. Frequent unexplained headaches, stomachaches or body aches are common, often with repeated visits to the school nurse or sick bay. Tests come back normal, and the aches continue anyway. Emotional numbness, feeling unable to feel anything at all, is a sign teens rarely volunteer.
Several of these signs look different in a teen than in an adult. That difference is exactly why adults, including doctors, so often miss them.
How Depression Looks Different in Teens and Adults
A depressed teen is more likely to seem angry than sad. Irritability or hostility is often the predominant mood, which is why teen depression gets mistaken for attitude. Adults expect that age group to be reactive and moody, so the symptoms hide in plain sight. A teen who is constantly grumpy, hostile and easily frustrated for weeks may be depressed, not rude.
Physical complaints differ as well. Depressed teens frequently report headaches or stomachaches that a physical exam cannot explain, while adults more often report fatigue and sleep changes. Teens are extremely vulnerable to criticism, rejection and failure, and over-achievers suffer from this most. Social patterns differ too: adults isolate fully, while teens usually keep some friends but pull away from parents or switch crowds.

| Symptom area | Typical in a depressed teen | Typical in a depressed adult |
|---|---|---|
| Dominant mood | Grumpy, hostile, easily frustrated | Persistent sadness |
| Physical complaints | Frequent headaches and stomachaches | Fatigue and sleep change |
| Reaction to criticism | Extreme sensitivity, needs constant reassurance | Withdrawal and self-blame |
| Social life | Keeps some friends, pulls away from parents, may change friend group | Isolates from almost everyone |
One exception trips up many families. An over-achieving teen who still tops the class can be depressed, and the signs show up as sensitivity and exhaustion rather than falling marks. A 94 percent average with tears after one lost mark can point to health problems, not perfectionism. Knowing the signs is not enough; a parent still needs a way to decide whether what they see is a rough patch or depression.
Three Questions That Separate Depression from a Rough Patch
A parent can usually tell the two apart by asking three questions: how long, how bad and how unlike themselves the teen is. Symptoms that last two weeks or longer, most days, cross the line from normal mood swings to possible teen depression. A diagnosis of major depression usually requires several symptoms during the same two-week period. Severity and change from the teen’s baseline fill in the rest of the picture.
A fourth question helps with borderline cases: does the teen seem able to manage difficult feelings, or does life seem overwhelming? A teen who cries over a breakup but studies for Monday’s test is coping. A teen who cannot get out of bed for that test is not. Time, intensity and function tell more than any single bad evening.
| What to look at | Normal mood swings | Possible depression |
|---|---|---|
| Duration | Hours to a day or two | Two weeks or longer, most days |
| Trigger | A clear cause: a fight, a test, a breakup | No clear cause, or a reaction far bigger than the cause |
| Interest in things they love | Returns once the mood lifts | Stays gone, hobbies dropped |
| School and friends | Minor dips, recovers | Steady decline in marks, attendance or friendships |
| Reachability | Can be talked to after the storm | Stays shut off or hostile for days |
An understandable trigger does not rule depression out. A failed exam or a grandparent’s death explains a low mood for a few weeks, and grief is normal. If the mood keeps going past that point and deepens instead of easing, the course matters more than the cause. Understanding what raises a teen’s risk helps a parent judge how seriously to take those borderline signs.
What Raises a Teen’s Risk of Depression
Depression has no single cause; it grows from a mix of biology, experience and environment. Brain chemistry, hormone changes, inherited traits, early trauma and learned patterns of helpless thinking all contribute, in different proportions for each teen. A parent who had depression when young should watch their own teen more closely, because the condition runs in families. Risk factors do not cause depression on their own, but they tilt the odds.
The factors also run in a loop. Substance use, family conflict and school trouble can be causes and consequences at the same time, each feeding the next. A parent who tries to work out which came first wastes energy that the teen needs now. The useful question is what is going on today, not what started it.
Family history and brain chemistry
Depression is more common in teens whose parent or grandparent has had it. Neurotransmitters, the chemicals that carry signals between brain cells, may work differently in a depressed teen. Hormone changes at puberty add to the mix. A pessimistic, self-critical personality or low self-esteem raises the risk depression carries, and a family member who died by suicide raises it further.
Bullying, trauma and stress
Long-term bullying or cyberbullying is one of the strongest risk factors, as is being a victim or witness of violence. Early childhood trauma such as abuse or the loss of a parent leaves a mark that can surface in the teen years. Recent stressful events, such as a parental divorce or the death of a loved one, can set off an episode. Family communication problems make everything harder to talk about.
In India, board exam pressure and coaching schedules act as ongoing stress rather than a one-off event. A Class 12 student juggling school, a coaching center and mock tests for two years has little room to recover. Other mental health conditions raise the risk too: anxiety, bipolar disorder, eating disorders, ADHD and a learning disability all appear on the list. Chronic illness such as diabetes or asthma, chronic pain, obesity, a traumatic brain injury and being LGBTQ in an unsupportive home also count.
Screens, social media and sleep
A study of 13,526 high school students found that three or more hours per school night on a digital device raised the odds of depressive symptoms. Social media can drag mood down in four ways: fear of missing out, constant comparison, less physical activity and disrupted sleep. Alcohol, nicotine or drug use adds a fifth drag that often starts with an online crowd. The most urgent signs of all deserve their own attention, because they can mean the teen is thinking about ending their life.
Suicide Warning Signs Every Parent Should Know
A depressed teen can be at risk of suicide even when the depression does not look severe from outside. The risk climbs higher when alcohol or drugs are involved, because they lower the brakes on an impulse. Every comment about dying, even one framed as a joke, must be taken seriously and acted on the same day. Treating “I’d be better off dead” as attention-seeking and letting it pass is the one mistake a parent cannot afford.
Warning signs that a teen may be planning to end their life include:
- Talking or joking about suicide, or saying “there’s no way out”
- Romanticizing death, or writing stories and poems about dying
- Reckless behavior or repeated accidents
- Giving away prized possessions
- Saying goodbye as if for the last time
- Seeking out weapons, pills or other means
When a teen is in danger, the next hour has a fixed order. Someone stays with the teen and does not leave them alone. A parent removes the means: lock up medicines, alcohol, knives and harmful household chemicals, in a lockbox if they cannot be removed. Then call 112 or take the teen to the nearest hospital emergency room if that can be done safely.
Help by phone is free and open all night. In India, the government’s Tele-MANAS helpline at 14416 answers round the clock, and the Vandrevala Foundation runs a 24-hour helpline at +91 9999 666 555. Families in the United States can call or text 988 to reach the 988 Suicide & Crisis Lifeline. That 988 suicide crisis service is free and confidential, with a Spanish line at 1-888-628-9454.
The suicide crisis lifeline model is the same everywhere: a trained person on the line within minutes. A parent should make sure a loved one nearby, an aunt or a close friend, knows the plan and can come over at once. Most situations are not emergencies, and the usual first move is a calm conversation.
How to Talk to a Teen Who Seems Depressed
A parent sits on the edge of the bed on a Sunday afternoon and says one honest sentence: “I’ve noticed you’ve stopped going to cricket, and I’m worried.” That is the whole opening, and it works better than a speech. Listening matters more than lecturing, and criticism or judgment shuts the conversation down within a minute. Talking about depression does not make it worse; silence does.
Most teens dislike being crowded with many questions, so the parent should name the changes, say why they worry, and then wait. A teen who shuts the parent out at first is not a closed door forever. Gentle persistence over several days usually gets further than one big confrontation. If the child will not open up, a trusted third party such as a school counselor, a favorite teacher or a mental health professional can help.

How to open the conversation
The first conversation goes best when it follows a simple order:
- Pick a calm, private moment: not right after an argument and not at a meal with relatives present.
- Name two or three specific observations: “You’ve skipped cricket three weeks in a row, and you’re up at 2 a.m.”
- Say why it worries them, in one sentence, with no diagnosis attached.
- Ask what is going on, then stay quiet and let the silence do the work.
- Offer a third person, a counselor or a doctor, if the teen prefers talking to someone else.
Parents often worry about making things worse by asking. The opposite happens: a teen who hears “I noticed” learns that someone is paying attention. That alone lowers the load a little, even when the teen says nothing back.
What not to say
Three phrases close a teen down fast: “in our time we had real problems”, “just focus on your studies” and “stop being dramatic.” Trying to argue a teen out of feelings with “things aren’t that bad” reads as not taking them seriously. Better lines are “that sounds really hard”, “I’m here even if you don’t want to talk yet” and “we’ll figure this out together.” A parent should make sure the teen hears that help is not a punishment.
One exception matters more than any phrase. A teen who says “nothing is wrong” but cannot explain the changes should still see a professional, and a parent should trust their gut. A parent does not need the teen’s agreement to seek an evaluation. Some signs mean the conversation should be followed by a call to a professional without delay.
When to Seek Help from a Mental Health Professional
A parent should seek professional help when the signs have lasted about two weeks, are getting in the way of school, friendships or sleep, or raise any safety concern. The two-week mark is enough to book a first visit; waiting for marks to recover or for the next vacation costs months. Symptoms are unlikely to improve on their own and may worsen if untreated. Untreated depression can lead to alcohol and drug misuse, academic problems, family conflict and suicide attempts.
Some signs mean the call goes out today, not after two weeks:
- Thoughts of self-harm, said aloud or written down
- Extreme fear, anxiety or anger toward themselves or others
- Feeling out of control
- Hearing voices or seeing things others do not
- Not sleeping or eating for three days in a row
- Behavior that friends, teachers or family raise concern about
In India, the path starts with a pediatrician or family doctor, who can rule out physical causes and refer onward. The next step is a child and adolescent psychiatrist or a clinical psychologist. A school counselor can suggest names, and the Tele-MANAS helpline at 14416 can also point a family toward a referral. Parents working out how to find a teen therapist should check credentials and ask about lower-cost options before the first session.
A mental health professional diagnoses depression after a mental health evaluation that may include talking to the family and teachers. The Mayo Clinic guide to diagnosis and treatment notes that a physical exam and lab tests may also be used to rule out other causes. A parent can prepare the teen by explaining that the first visit is mostly conversation, not needles.
The health professional will usually help the family write an emergency plan. The teen should save emergency numbers in their phone before leaving the clinic. Knowing what treatment involves makes that first appointment far less frightening.
Treatment Options for Teen Depression
Most teen depression is treated with talk therapy first, antidepressant medication added only when needed, and family and school brought in alongside. The choice depends on the teen’s symptoms, age, general health and how severe the depression is. Many teens who get treatment improve within weeks, and continued treatment after symptoms ease helps prevent relapse. The teen should have a say in choosing the specialist, and a poor fit with a therapist is a reason to look for another.
A parent should not feel pushed into medication because therapy seems expensive or slow. Before agreeing to any plan, the right questions are what each option costs, how long it takes and what happens if it fails. Unless the teen is acting dangerously or at risk of suicide, there is time to weigh the types of treatments. Information from the doctor, written down, makes the decision easier at home.
| Treatment | Usually used for | What it involves | What to watch |
|---|---|---|---|
| Talk therapy | Mild to moderate depression | Weekly sessions, CBT or similar, in person or online | Finding a good fit may take patience |
| Antidepressant | Moderate to severe, or when therapy alone is not enough | Prescribed by a psychiatrist, monitored closely | Higher suicidal-thought risk in first two months; never change the dose alone |
| Family therapy | Family conflict or communication problems | Sessions with parents and teen | Requires parents to participate, not just the teen |
| School assistance | Academic decline or attendance trouble | Counselor support, workload adjustments | Needs the school informed; decide with the teen who knows |
Talk therapy
Talk therapy is often the first treatment for mild to moderate depression. It helps a teen change distorted views of themselves, identify stressors and work through hard relationships. Common approaches include CBT, DBT and psychodynamic therapy. A 2025 systematic review of 27 studies found that online therapy could reduce depressive symptoms in teens, useful when the nearest therapist is hours away.
Teens have questions of their own, and the questions teens most often ask about therapy cover confidentiality, what a session looks like and how to pick a therapist. Learning that a therapist keeps most things private, except when safety is at risk, often lowers resistance. A hesitant teen may agree to one online session before anything else.
Antidepressant medication
An antidepressant may be warranted if therapy alone does not resolve the depression, and it works best alongside therapy, never instead of it. These drugs were designed and tested on adults, and they can increase suicidal thinking and behavior in some teens, with the risk highest in the first two months. Teens with bipolar disorder, a family history of it, or a previous suicide attempt are particularly vulnerable. The psychiatrist monitors effectiveness and side effects, and nobody changes the dose without that doctor.
An antidepressant is never a shortcut around therapy. The first two months need close watching, and no one adjusts the dose on their own.
Family and school support
Family therapy gives the teen hope and self-worth and helps the whole household change how it talks. It only works when the parents attend too, rather than sending the teen alone to be fixed. School counselors and school psychologists can act as advocates, arranging lighter workloads or extra time on tests. Which teachers get told is a decision to make with the teen, not for them.
Treatment works best when daily life at home supports it. The routines that do that are small and repeatable.
Everyday Support That Helps a Teen Recover
A 20-minute walk together after dinner doubles as the day’s conversation and the day’s exercise. It costs nothing and asks nothing of the teen except company. Isolation makes depression worse, so daily distraction-free face time matters more than any supplement or app. Treatment instructions and appointments must be followed exactly: every session kept, every medicine given as prescribed, every change tracked.
Routines that support recovery look ordinary from the outside:
- A fixed daily unhurried chat, even ten minutes with the phones put away
- A sleep routine aimed at 9 to 10 hours, with the phone charging outside the bedroom
- An hour of movement a day, from walking the dog to cycling or dancing
- Regular home-cooked meals with protein, healthy fats and fresh produce, fewer sugary and starchy snacks
- One in-person social activity a week: a friend over, a club, a sports practice
- Screen-free family time, with the parent setting the example first
Activities that match the teen’s interests, whether art, dance, music or a sports team, help them re-engage, and volunteering boosts self-esteem. Recovery is bumpy, with small victories and setbacks, so a bad Tuesday after a good week is not failure. A parent should call the doctor if the sadness returns or worsens rather than waiting for the next appointment. Encouragement to meet friends in person beats any amount of nagging about the phone.
A parent who burns out helps no one. Their own sleep, support from friends or a support group, and their own therapy if needed are part of the plan, because the parent’s mental health carries the household. Siblings also need time and attention, since a home organized around one child’s illness quietly costs the others. The parent now holds the full picture, from the first sign to recovery.
Conclusion
No parent needs to diagnose their teen alone. The difference between normal mood swings and teen depression comes down to how long, how bad and how unlike themselves the teen is, with two weeks as the line. A mood that lifts by dinner is adolescence. A mood that has not lifted in a fortnight is a reason to act.
Depression is treatable, and most teens improve within weeks of starting help. Parents who ask early give their child the shortest road back. The mental health system in India is reachable: a family doctor, a school counselor or a helpline can open the door.
Tonight, the parent should write down the specific changes noticed in the last two weeks, in plain words. If the list runs longer than a few lines, book a visit with the pediatrician or family doctor this week.